

What Dr Hoskins treats in the knee
Most people who come to the rooms about a knee arrive with one of three things: pain from osteoarthritis that is no longer controlled by non-surgical treatment, a knee replacement that is not behaving as it should, or a fracture involving the knee.
Knee replacement is core to the practice and it is also Dr Hoskins’ main research area. He has published on component alignment, knee phenotype, constraint and bearing choice, and on when a stem should be added to a primary knee replacement. Revision knee replacement is a distinct subspecialty within that, and he co-authored textbook chapters on revision technique for both Springer and Elsevier.
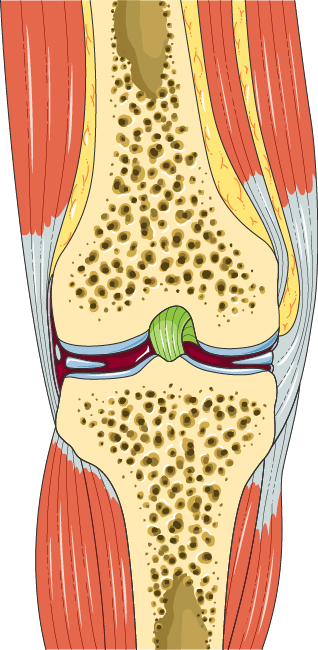
The thigh bone and shin bone meet through two cartilage-covered surfaces, separated by the menisci and held in line by the ligaments and the muscles either side.
Knee arthritis, knee replacement and fractures involving the knee are all problems of these structures.
How a knee assessment works
An appointment starts with your history and an examination, alongside any imaging you already have. In many cases that is enough to explain what is happening and to talk through the options. Sometimes further imaging is needed before a plan can be settled.
Surgery is one option among several, and it is not always the right one at the point you are first seen. A consultation is as likely to result in a plan for non-surgical management, or a decision to review you again later, as it is to result in an operation.
What is tried before surgery
Many knee problems are managed well without an operation. Where it is appropriate, non-surgical care may include:
- Activity modification and pacing
- Weight management
- Physiotherapy and targeted strengthening
- Pain relief and anti-inflammatory medication where appropriate
- Walking aids where they help
- Joint injections in selected cases
Surgery is considered when pain is interfering with your quality of life and is no longer adequately controlled by other measures, not simply because a scan shows wear.
If an operation is recommended, you are given the benefits, the risks and the likely recovery, with time to decide. There is no obligation to decide on the day.
The knee operations offered here
The knee side of the practice is joint replacement and fracture surgery. In outline, that covers:
- Assessment and non-surgical management of knee osteoarthritis
- Total knee replacement
- Complex primary knee replacement, where deformity, stiffness, previous surgery or bone loss make a first replacement harder than usual
- Revision knee replacement, including for loosening, wear, stiffness, instability or infection
- Fractures involving the knee, and fractures around an existing knee replacement
The unhappy knee replacement
Some people are left with a knee replacement that has not delivered what they hoped for: pain that never settled, stiffness, swelling, a feeling of instability, or a knee that simply does not feel right. It is more common than most people expect, and it deserves a structured assessment rather than reassurance alone.
The assessment is systematic, because the possible causes are many and they are treated quite differently. It looks for infection, which can be low grade and easy to miss; loosening or wear of the components; instability or stiffness; problems with alignment or the kneecap; and pain referred from elsewhere, most often the hip or the spine. Blood tests, X-rays, and sometimes further imaging or sampling of the joint fluid each have a place.
Two findings matter as much as any diagnosis. Sometimes a cause is clearly identified and can be addressed, which may mean revision knee replacement. And sometimes no surgical cause is found, in which case the honest advice is usually not to operate: revision surgery performed for unexplained pain often does not relieve it, and Dr Hoskins will say so plainly.
Dr Hoskins performs revision knee replacement and has published research on how and why knee replacements fail. Second opinions are welcome, including for knee replacements done elsewhere.
How the surgery is planned
Surgery planned around you. Dr Hoskins takes a patient-centred approach to knee surgery. The surgical approach is chosen to suit the individual, their anatomy, diagnosis, activity level and goals, rather than a single fixed technique.
Patient-specific implant selection. Implants and constructs are selected for each patient rather than defaulting to one brand or design, so the choice fits the person’s joint, bone quality and needs.
Technology-assisted where it adds value. Where it adds value, Dr Hoskins uses technology-assisted techniques during joint replacement to support accurate implant positioning and alignment. The approach, implant and any technology used are selected to suit each patient.
Where surgery happens, and how it is paid for
Consulting is in Whangārei. Private surgery is carried out at Allevia Kensington, and Dr Hoskins also operates at Whangārei Hospital.
A knee injury is generally covered by ACC, and surgery for it usually needs ACC approval first. Knee arthritis and elective knee replacement are generally not ACC funded, so the routes are the public system, private health insurance, or self-funding. Consultation and surgery fees are given to you when you book, and you receive a written estimate before any operation. See ACC, insurance and fees for the detail.
Do I need a referral?
Yes. Appointments are made by referral from your GP or another health professional, and physiotherapists can refer directly as well. If you have an ACC claim, your referrer will note that on the referral. See your appointment for what to expect, and ACC, insurance and fees for how the funding side works.